
“Normal” imaging does not mean imagined pain
MRI and X-ray show structure at one moment. They may not fully capture dynamic instability, nerve irritation, muscle coordination, sensitization or the specific movement that triggers symptoms. A reassuring scan narrows possibilities; it does not cancel what you feel.
“Abnormal” imaging does not automatically identify the cause
Systematic reviews have found common findings in people without symptoms. In asymptomatic knees, pooled estimates included cartilage defects in 24% overall and meniscal tears in 10%; among adults 40 and older, estimates rose to 43% and 19%. In asymptomatic spines, age-related findings also become increasingly common. A population study of 664 people found that most detected rotator-cuff tears were asymptomatic.
The useful question is not only “What does the MRI show?”
It is “Does this finding match the location, timing, examination and function—and will acting on it change the outcome?”
How we build a working diagnosis
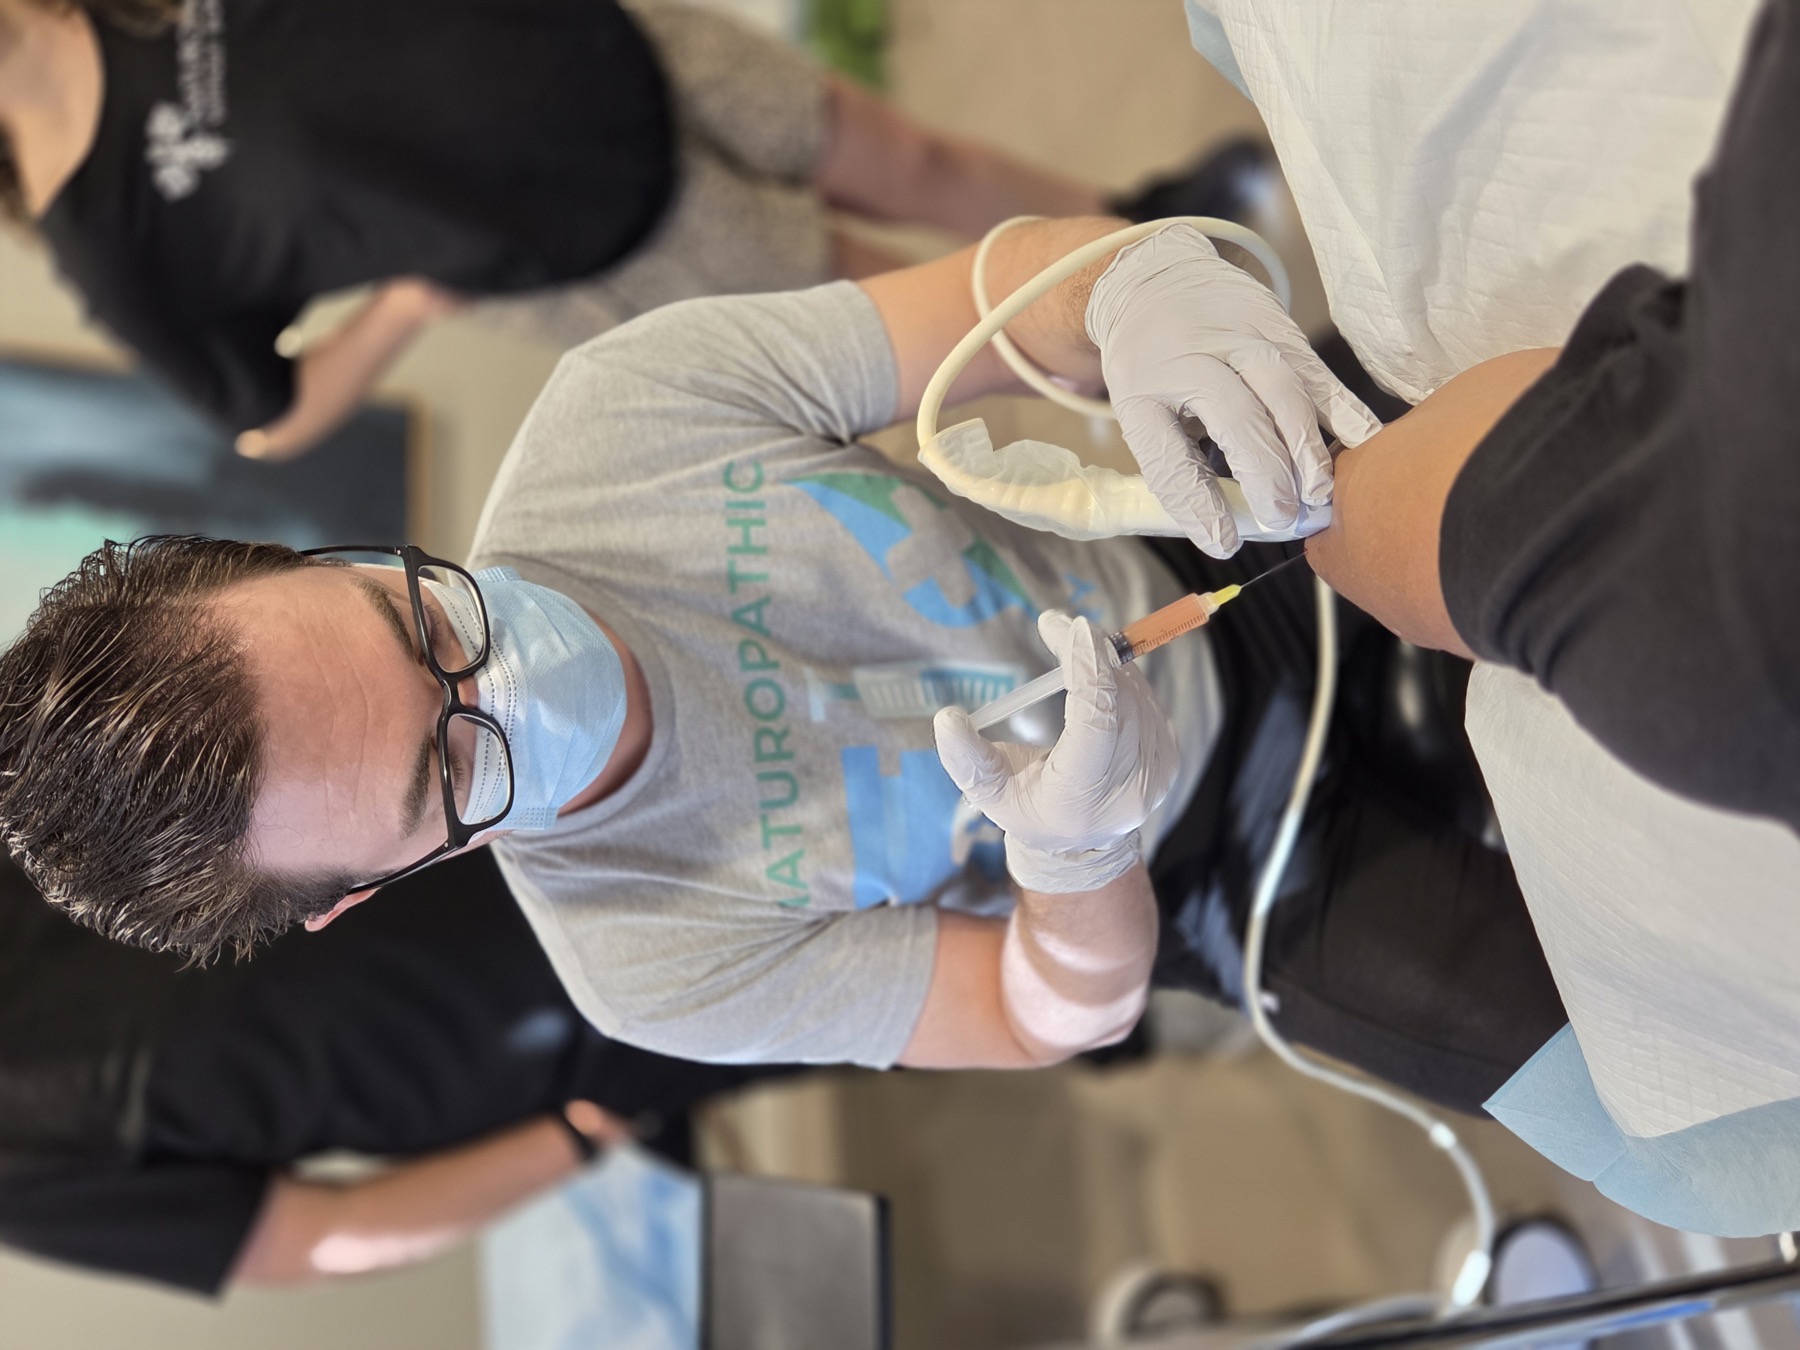
We start with the timeline and what you are trying to regain. The examination may assess movement, strength, stability, tissue loading and nerve sensitivity. Musculoskeletal ultrasound can add a real-time view of selected tissues. Occasionally, a carefully chosen diagnostic injection helps test whether a suspected structure is actually driving symptoms.
Function is an outcome—not an afterthought
A follow-up scan can matter in some conditions, but progress is often better measured by capacity: walking, lifting, sleeping, training, working and trusting the body again. Tissue health and symptoms do not always improve on the same timetable.